
BACKGROUND
Physical activity plays an important role in a healthy lifestyle. Research shows that regular training is necessary for maintaining good physical and mental health (e.g., Warburton & Bredin, 2017). Between 2000 and 2022, a significant increase in the number of insufficiently physically active individuals was observed, and it is estimated that 31.3% of the global population currently falls into this category (Strain et al., 2024). Research conducted in 28 EU countries showed that 46% of respondents never exercise or play sport (TNS, 2018). Moreover, among physically active individuals, 75% report attempting to exercise but having difficulties to maintain motivation (Mind & Roses & IRCenter, 2024). Therefore, support of physical activity engagement is highly recommended, and more research on this issue is needed.
This recommendation is addressed by psychological interventions, which seek not only to strengthen individuals’ motivation to engage in physical activity (Knittle et al., 2018) but also to bring about changes in beliefs and experiences associated with health-promoting behaviors. One potential approach is an intervention known as mental contrasting with implementation intentions (MCII; Oettingen et al., 2013). The effectiveness of MCII has been demonstrated in promoting various health-related behaviors (see Gollwitzer & Oettingen, 2019; Wang et al., 2021). However, there is limited evidence concerning the effects of MCII in healthy individuals who wish to increase their physical activity. The present research seeks to address this gap by testing the effectiveness of short online MCII intervention in increasing daily walking and aerobic training.
Theoretical background
MCII helps people to commit to their goals and take action towards them (Oettingen et al., 2013). It combines two complementary phases: mental contrasting (MC; Oettingen, 2012) and implementation intentions (II; Gollwitzer & Sheeran, 2006). MC starts by identifying a personally important, challenging yet feasible wish for the future and imagining a desired future (e.g., walking 3 km every day). It is continued by identifying and imagining the present inner obstacles that stand in the way of achieving the desired future (e.g., being discouraged by bad weather). Examining the potential internal obstacles after envisioning a positive outcome helps one understand the obstacles and think about whether and how to overcome them. This leads to goal commitment and provides the energy needed to realize the desired future (Oettingen et al., 2009). Phase II supplements this process with the formation of “if-then” plans specifying how to respond to identified inner obstacles (Gollwitzer, 2018). Compared to goal intentions alone, such plans increase the likelihood of goal attainment (Gollwitzer & Sheeran, 2006). They automate respective goal-directed responses, thus reducing the need for deliberation about appropriate responses to a critical situation. As a combination of MC and II strategies, MCII is expected to multiply the effects of each strategy, helping people to set and achieve challenging yet realistic goals (Oettingen et al., 2013).
MCII as a goal-realization strategy was a base for interventions (popularized with the acronym WOOP: wish, outcome, obstacle, plan; Wittleder et al., 2025), and its effectiveness has been demonstrated in many domains, including health behaviors change (see Gollwitzer & Oettingen, 2019). The meta-analysis based on 21 empirical studies demonstrated small to medium effect size effects of MCII (Wang et al., 2021). These effects were stronger for studies with interventions based on interactions between participants and experimenters (g = 0.465) than for studies based on documents (g = 0.277) which included completing the intervention online. However, the evidence concerning online MCII is limited, and only three studies related to health behavior change were identified.
Delivering MCII online has advantages and disadvantages. On the one hand, online interventions are cost effective and let participants apply MCII on their own, at their own pace. They enable participants to anticipate the most relevant personal obstacles and link them to personalized responses, without being influenced by social approval. On the other hand, participants of the online intervention may generate inadequate outcomes, formidable obstacles, or ineffective plans for overcoming these obstacles (Kizilcec & Cohen, 2017), which might decrease the MCII effects. Despite the development of dedicated mobile applications (see https://woopmylife.org), few studies have tested the effectiveness of the MCII delivered online. For example, a brief online MCII intervention was effective in reducing cigarette smoking at high – but not low – levels of cigarette dependence (Mutter et al., 2020). Definitely, more research is needed to test online delivered MCII effectiveness.
There is some initial evidence that MCII helps people to increase their physical activity; however, the evidence is limited to very specific samples. For example, MCII was documented to improve exercising in patients with schizophrenia (Sailer et al., 2015), stroke survivors (Marquardt et al., 2017), or sedentary, disadvantaged adults (Abbott et al., 2020). Some research has provided mixed results; for example, a study demonstrated a significant increase of physical activity for men but not for women (Liau et al., 2018). All this evidence is promising, but limited. In particular, the effectiveness of the online MCII in promoting physical activity in general population should be tested. Our two studies aimed to fill this gap.
Present research
The research examined the effectiveness of online delivered MCII among healthy individuals who reported a desire to increase their physical activity. We concentrated on two physical activity parameters – daily step count and time spent on aerobic training – and on other psychological variables, as explained below.
One of the primary indicators of daily physical activity is the number of steps taken per day. Recent systematic reviews have demonstrated that maintaining a regular daily step count contributes to improved physical health and reduces the risk of cardiovascular diseases and mortality (Ding et al., 2025). Taking this into account, we aimed at increasing daily steps in young people, who do not usually engage in enough physical activity (Górna et al., 2023).
Another form of activity among physically active individuals is aerobic training, commonly referred to as ‘cardio’. It is considered a fundamental component of physical fitness; it involves prolonged, repetitive activity aimed at increasing aerobic capacity (e.g., cycling or running; Knuttgen, 2007). Regular participation in aerobic training provides physical health benefits, including a reduced risk of cardiovascular disease (Miele & Headley, 2017) and mental health benefits (De Geus & Stubbe, 2007). Moreover, regular cardio exercise contributes to body weight management and improvements in body composition (Wu, 2023), which are key parameters in gym-based training. Consequently, we aimed to examine the effectiveness of MCII in increasing the amount of time devoted to aerobic training by people training at the gym.
Beyond measures of physical activity, we assessed psychological effects of MCII, concentrating on sport and physical activity-related constructs, such as sport engagement, sports training self-efficacy, and physical activity-related affect (both positive and negative). Sport engagement refers to a positive, motivational state associated with participation in physical activity, which is manifested through vigor, dedication, and absorption (Stolarski et al., 2020). Sports training self-efficacy is a specific type of sports self-efficacy which refers to an individual’s confidence in their ability to complete training tasks and achieve established training goals (Zhao et al., 2026). Physical activity–related affect refers to both positive and negative consciously accessible feelings that are focused on a specific object (Mielniczuk & Łaguna, 2018), namely, on physical activity.
Study 1
Study design and intervention
Measurements were taken at three time points: before the intervention (baseline, T1), one week after the intervention (T2), and two weeks after the intervention (follow-up, T3). Participants were randomly assigned to either an experimental or a control group. All participants were presented with a short text highlighting the importance of regular physical activity. Only participants in the experimental group, however, were guided through the MCII procedure, which was delivered online via a dedicated form, where participants entered their own responses (see Supplementary materials). We strictly followed the MCII protocol (see https://woopmylife.org). Screening of participants, measurements, and the intervention were conducted via an online platform and delivered in Polish.
A priori power analysis in G*Power (α = .05, β = .90, f = 0.25, r = .50) for a mixed design with two groups and three repeated measurements indicated a final minimum total sample size of 36 participants. Those who completed all three measurements were entered into a prize draw consisting in each study of 20 rewards valued at PLN 50 each. The procedure received approval from the ethics committee at the authors’ university.
Participants
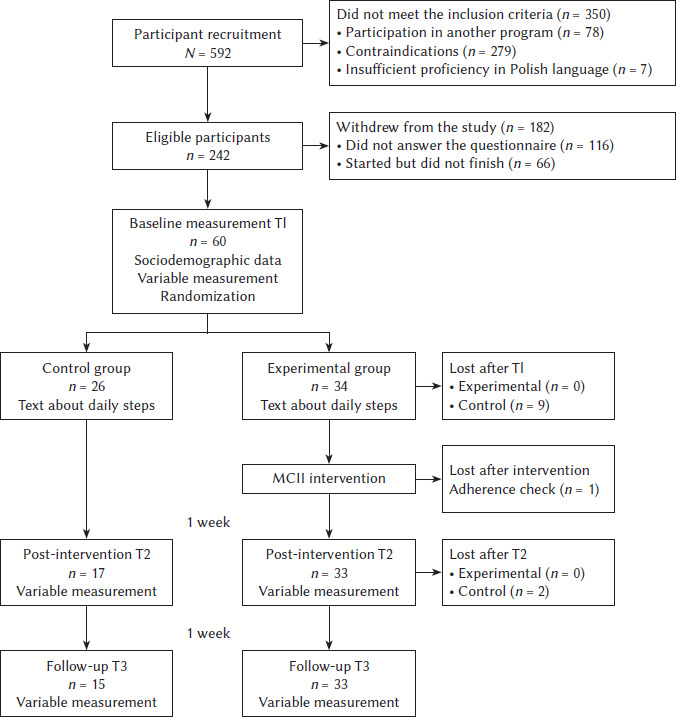
The final T1 sample consisted of 59 participants (nExp = 33, nContr = 26). This yielded 177 observations, of which 157 (88.7%) contained no missing values. Participants’ age ranged from 17 to 35 years (M = 20.22, SD = 3.53); 66.1% of them were women.
Procedure
Participants were recruited among university students and adult secondary school students. The eligibility criteria for participation in the study (as verified by questions with yes/no answer) were: (1) willingness to increase daily step count, (2) no concurrent participation in another program aimed at increasing daily step count, (3) absence of any of seven health-related contraindications (see Measures section), and (4) fluency in the Polish language. Only those who met all of the above criteria were invited to take part in the study.
Of the 592 individuals who took part in the recruitment process, 242 were ultimately considered eligible to participate in the study; however, only 60 participants completed the T1 questionnaire (Figure 1). They were allocated to the experimental (MCII) or control group. After the intervention, the adherence to the MCII protocol was evaluated by two independent judges reading participants’ answers to instructions, and those who did not adhere to the procedure (provided meaningless responses) were excluded from the analysis (1 student).
Measures
During screening, to assess health-related contraindications for engaging in physical activity, we used seven questions from the Physical Activity Readiness Questionnaire (PAR-Q; Warburton et al., 2011). These questions refer to the previous seven days and address various exercise-related risks. Participants responded to each question with yes/no answers. Answer yes to one or more questions was treated as an indicator of health-related contraindications.
At three time points the participants filled in measures described below, with instructions to concentrate on experiences from the past week (seven days). The reliability ranged from acceptable to excellent, indicating satisfactory internal consistency across all methods. The CFA results indicated good or acceptable model fit. Detailed results are provided in Supplementary materials, Tables S1 and S2.
Daily step count was assessed using a mobile phone application (StepsApp). During the face-to-face meeting, participants were given detailed instructions on how to correctly install the application and interpret its results. They were also instructed to disable notifications, because these could confound the study results by providing additional cues to increase physical activity. At each measurement time, participants recorded their daily step counts for the preceding seven days using a dedicated calendar (see Mutter et al., 2020), based on the values displayed in the application.
Sport engagement was measured using nine items from the Polish version of the Sport Engagement Scale (Stolarski et al., 2020). The items assessed feelings related to engagement in physical activity (e.g., “When I woke up in the morning, I couldn’t wait to start my training.”), rated on a scale ranging from 1 (almost never) to 7 (always).
Sports training self-efficacy was measured using the Sport Training Self-Efficacy Scale including four items from a modified Polish version of the General Self-Efficacy Scale (GSES; Juczyński, 1999). The items were modified to include the phrase ‘in training’ and were presented in the past tense (e.g., “It was easy for me to stick to my training goals”). Participants responded on a four-point scale (1 – no, 2 – rather no, 3 – rather yes, 4 – yes).
Positive and negative activity-related affect was measured using the Polish version of the Affective Well-Being measure (Mielniczuk & Łaguna, 2018), adapted to assess emotions associated with physical activity (“Thinking about the past week, indicate how often physical training made you feel the following emotions”). The measure consisted of 12 adjectives (e.g., “optimistic”, “depressed”) rated on a scale from 1 (never) to 6 (always).
Data analysis
Given the longitudinal structure of the data and non-independence of observations, we applied linear mixed-effects models (LMMs), which appropriately account for within-subject correlations and allow the inclusion of incomplete cases (West et al., 2014). The model specified group (experimental and control), time (T1, T2 and T3), and their interaction as fixed effects, and included a random intercept for participants. Model parameters were estimated using restricted maximum likelihood, which provides less biased variance estimates in mixed models (Pinheiro & Bates, 2000). When significant effects were observed, post hoc comparisons of estimated marginal means were performed with Bonferroni correction to control for multiple testing. All analyses were conducted using IBM SPSS Statistics (version 29).
RESULTS
Descriptive statistics for all variables across three measurement points are presented in Supplementary materials, Table S2. Mean values suggested modest fluctuations of all variables over time in both the experimental and control groups; however, no clear systematic group differences were observed.
To formally test changes over time and between groups, LMMs with random intercepts for participants were conducted for each outcome variable separately. Before the main analyses, the distributions of the outcome variables were visually inspected using histograms and box plots. Moderate skewness was observed; however, no extreme values or severe deviations were identified that would be expected to substantially affect model estimation. For all variables, variance estimates of the random intercepts indicated considerable between-person variability, supporting the use of LMMs. For the psychological outcomes, estimates ranged from 0.02 to 0.24, whereas the behavioral outcome measured showed a substantially larger variance estimate (3819366), which was expected taking into account measurement specificity. The results of LMMs revealed no statistically significant main effects of group or time (p < .05) for all outcome measures. Moreover, no significant group × time interactions were observed (p > .05), indicating that changes over time did not differ between the experimental and control groups. Detailed results are provided in Supplementary materials, Table S3. The results indicate that the online version of MCII did not increase the number of daily steps taken by young people and did not change any of the psychological variables.
Study 2
Study design and intervention
The study design and intervention (see Supplementary materials) were the same as in Study 1.
Participants
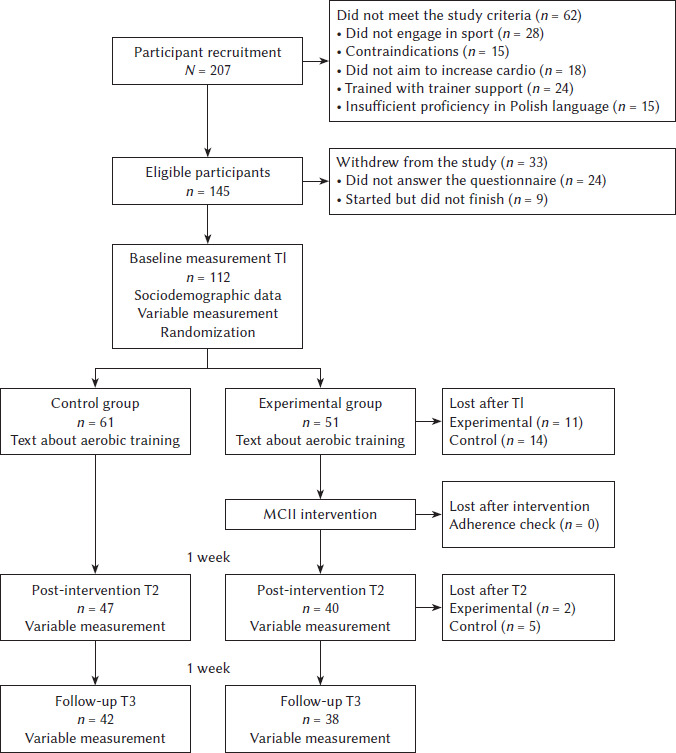
The final sample consisted of 112 participants (nExp = 51, nContr = 61). This resulted in 336 observations, of which 279 (83%) contained no missing values. Participants’ age ranged from 16 to 55 years (M = 25.68, SD = 6.91); 58% of them were men.
Procedure
Participants were recruited in Poland from people training at the gym. The inclusion criteria for participation in the study (each verified with a single each yes/no question) were: (1) willingness to increase daily time spent on aerobic training, (2) engaging in physical training at a recreational (amateur) level, (3) training not under the supervision of a coach, (4) absence of health-related contraindications that prevent aerobic training, and (5) fluency in the Polish language. Only those who met all of the above criteria were invited to take part in the study.
Of the 207 individuals who took part in the recruitment process, 145 were found eligible to participate in the study, and 112 participants completed the T1 questionnaire (Figure 2). They were randomly allocated to the experimental or control group. Evaluation of intervention adherence showed that all participants who completed the intervention properly fulfilled the MCII protocol.
Measures
To measure time spent on aerobic training during each measurement, participants were presented with a calendar displaying the days of the previous week (Mutter et al., 2020). For each day, they entered the number of minutes devoted to aerobic training. Participants were informed about this procedure one week in advance so that they could record the duration of their training sessions. Finally, the average daily time spent on aerobic training was calculated.
The same psychological variables as in Study 1 were measured using the same measures, except that we used six items to measure sports training self-efficacy. Reliability coefficients were acceptable to excellent, and validity analyses indicated acceptable to good indicators (see Supplementary materials, Tables S1 and S2).
RESULTS
Descriptive statistics for all variables across the three measurement times are presented in Supplementary materials, Table S2. Inspection of the mean values indicates minor changes in the variable over time in both the experimental and control groups; however, these changes are not systematic.
LMMs (see Supplementary materials, Table S3) for aerobic training, sports training self-efficacy, and physical activity-related negative affect revealed no statistically significant main effect of group, time, or group × time interaction (p > .05). A significant main effect of group was observed for sport engagement F(1, 105) = 4.14, p = .044, and positive affect F(1, 107) = 5.80, p = .018. Bonferroni-adjusted pairwise comparisons indicated higher overall results in the experimental group compared to the control group, averaged across time. However, no significant effects of time or group × time interaction were found for engagement and positive affect, suggesting that the intervention did not significantly influence the outcomes. Random intercept variance estimates indicated substantial between-person variability across all outcomes (0.16-0.80 for psychological outcomes; 47 135 for cardio). As expected, the variance estimate was considerably larger for the cardio measure.
Discussion
Our aim was to examine the effectiveness of a short MCII intervention (Oettingen, 2015) delivered online to healthy people desiring to increase their physical activity levels. In two experimental studies we tested the effects of MCII on the daily step count in young people (Study 1) and time spent on aerobic training in people training at the gym (Study 2). We also measured sport engagement, sports training self-efficacy, and positive and negative affect related to physical activity, expecting that the MCII intervention could lead not only to behavioral outcomes but also to changes in physical activity-related beliefs and affect. Despite careful research design with three measurements and sample sizes that guarantee statistical power, the results of both studies showed no statistically significant intervention effects. This indicates that the online MCII intervention did not produce detectable improvements in physical activity, physical activity-related beliefs, or affective outcomes.
Previous studies indicated that in different domains, MCII face-to-face interventions may produce larger effects than online interventions; however, even delivered online MCII resulted in small-to-medium effects on behavior change (Wang et al., 2021). Our nonsignificant effects may be due to two reasons: individual online work may result in formulating lower quality MCII strategies (Kizilcec & Cohen, 2017) and lower commitment to the intervention (Knittle et al., 2018). First, although we tested adherence to the intervention protocol (Beintner et al., 2019), the quality of MCII strategies formulated online might still differ from those developed in face-to-face contact. Second, although the intervention included active components that require engagement (i.e., answering in writing), more engaging than ‘passive’ interventions (e.g., reading assignments; Beintner et al., 2019), commitment to online interventions might still be lower than commitment to face-to-face interventions. We tested the commitment before the intervention by asking whether participants were motivated to improve the selected parameter of physical activity, and only those who confirmed their motivation were invited to take part. However, people were invited to both interventions, and they did not actively search for an online intervention, which may have reduced their commitment. Even when intervention fidelity is ensured in online interventions through standardized delivery according to the protocol, the lower commitment of participants may reduce intervention effectiveness.
Implications
Based on the results of our studies, we recommend the face-to-face rather than the online MCII intervention format, as some preliminary studies demonstrated their effectiveness. However, because this evidence come from specific, mostly clinical, samples (Marquardt et al., 2017; Sailer et al., 2015; Stadler et al., 2009) or demonstrates intervention effectiveness for some participants only (e.g., increase of physical activity for men but not for women; Liau et al., 2018), more research is needed to test whether MCII may be effectively used to promote physical activity in the general population. This is of great importance taking into account the significance of physical activity for maintaining physical and mental health (Warburton & Bredin, 2017) and insufficient engagement in this activity in the population (Strain et al., 2024). Efficient support for motivation to engage in physical activity is therefore needed (Knittle et al., 2018), and effective psychological interventions may provide a solution. However, the effectiveness of such interventions needs to be evaluated.
Limitations and future research directions
Our research contains limitations which may be addressed in future studies. First, we used the single session MCII protocol. To increase engagement of participants, the duration of online MCII intervention may be extended or multiple sessions may be provided. This may help to maintain the motivation of participants and result in effective behavior change (Knittle et al., 2018), which should however be tested in future studies.
Second, to evaluate potential health risks of increased physical activity, we applied the PAR-Q (Warburton et al., 2011) as a widely used instrument employed in other studies on MCII effectiveness (e.g., Liau et al., 2018). People who responded positively to one or more of the seven PAR-Q questions, indicating potential health risks associated with increasing physical activity, were not invited to participate in the study. The PAR-Q, however, is “purposely conservative, leading to many false positive results” (Bredin et al., 2013) and may therefore result in unnecessary exclusions from interventions aimed at increasing physical activity. As in the case of youths participating in Study 1, about 47% of them reported some issues (e.g., chest pain during physical activity), although such responses may not necessarily indicate an increased health risk associated with walking. Future studies may consider whether less restrictive eligibility criteria are appropriate when interventions target moderate-intensity physical activity, while ensuring participant safety.
Third, in Study 1 we used a mobile phone application to count daily steps, given the low compliance with wearing special devices, such as accelerometers (Ruissen et al., 2018). However, participants may not always carry their mobile phones while walking, potentially leading to underestimation of step counts. In Study 2, we used time spent on aerobic training as an indicator. Future studies could consider using additional or more objective measures of physical activity.
CONCLUSIONS
In two experimental studies, we found no statistically significant effects of a brief online MCII intervention on physical activity change and other psychological variables in participants from the general population. As only a limited number of studies have examined the effects of MCII in the context of physical activity and sport, further research in these settings is warranted. Both face-to-face and online versions of MCII should be investigated further.
Supplementary materials are available on the journal’s website.

